Mitral regurgitation can develop gradually. Some people are told they have a “leaky valve” during a routine echocardiogram and feel almost normal for years. Others develop breathlessness, fatigue, swelling or repeated heart-failure symptoms as the leak becomes more severe.
The challenge is knowing when observation is still appropriate and when the valve problem has reached a point where treatment should be discussed. For selected patients, one treatment option is transcatheter edge-to-edge repair, commonly known as TEER, using a device such as MitraClip.
MitraClip is not appropriate for every person with mitral regurgitation. The timing depends on the cause of the leak, its severity, symptoms, heart function, valve anatomy and the risks of surgery.
What Does Mitral Regurgitation Do to the Heart?
The mitral valve sits between the left atrium and left ventricle. It should close during each heartbeat so blood is pushed forward into the aorta.
When the valve does not seal properly, some blood moves backward into the left atrium. The heart may compensate for a long time by enlarging or pumping harder. Eventually, the extra volume can contribute to enlargement of the atrium and ventricle, pressure in the lungs, atrial fibrillation and heart failure.
This is why a patient may feel relatively well even while the valve problem is progressing.
Primary vs Secondary Mitral Regurgitation
The cause of mitral regurgitation affects treatment.
Primary mitral regurgitation comes from a structural problem in the valve itself. A leaflet may prolapse, a supporting chord may rupture or degenerative changes may prevent the valve from closing correctly.
Secondary mitral regurgitation develops because the heart muscle or atrium changes shape. The leaflets may be structurally normal, but enlargement of the ventricle or atrium pulls the valve apart so it cannot seal properly.
These two forms can look similar on a basic report but may require very different treatment strategies.
Symptoms That Deserve Attention
Breathlessness with activity is one of the most common symptoms. Patients may notice they can no longer walk as far, climb stairs as easily or complete household tasks without stopping.
Other symptoms can include fatigue, swelling of the legs or abdomen, palpitations, difficulty lying flat because of breathlessness or repeated admissions for fluid overload and heart failure.
Symptoms should be discussed with a cardiologist rather than assumed to be a normal part of ageing.
Why Echocardiography Matters
An echocardiogram measures how severe the regurgitation is and provides information about the size and function of the heart.
When a catheter procedure is being considered, transoesophageal echocardiography often provides more detailed views of the mitral leaflets and the exact location of the leak.
The Heart Team uses this imaging to decide whether a TEER procedure is technically possible and whether reducing the leak is likely to provide meaningful benefit.
When Is MitraClip Considered?
MitraClip may be considered for selected patients with severe mitral regurgitation when the anatomy is suitable.
For primary mitral regurgitation, surgery remains an important treatment, particularly when a durable surgical repair can be achieved with acceptable risk. TEER becomes especially relevant when a patient is at high surgical risk or surgery is considered unsuitable.
For secondary mitral regurgitation, doctors first optimise treatment for the underlying heart condition. This can include guideline-directed heart-failure medicines and, in suitable patients, cardiac resynchronisation therapy.
If severe regurgitation and significant symptoms remain despite appropriate treatment, selected patients may benefit from TEER.
Why Medical Treatment Comes First in Secondary MR
Secondary mitral regurgitation is often a consequence of heart failure rather than an isolated valve problem. Improving the function and loading conditions of the left ventricle can sometimes reduce the severity of the leak.
That is why a patient should not be rushed directly to a clip procedure without careful heart-failure evaluation.
A heart-failure specialist, imaging cardiologist and structural heart team may all contribute to deciding whether the valve is now an important treatment target.
What Makes a Valve Suitable for MitraClip?
The device needs enough leaflet tissue to grasp securely. The team also evaluates calcification, valve area, leaflet motion and the location and width of the regurgitant jet.
If the anatomy is unfavourable, the procedure may not reduce the leak adequately or could create too much narrowing of the mitral valve.
Patients considering MitraClip in Mumbai should expect detailed imaging and a clear explanation of whether their valve anatomy is suitable.
What Happens During the Procedure?
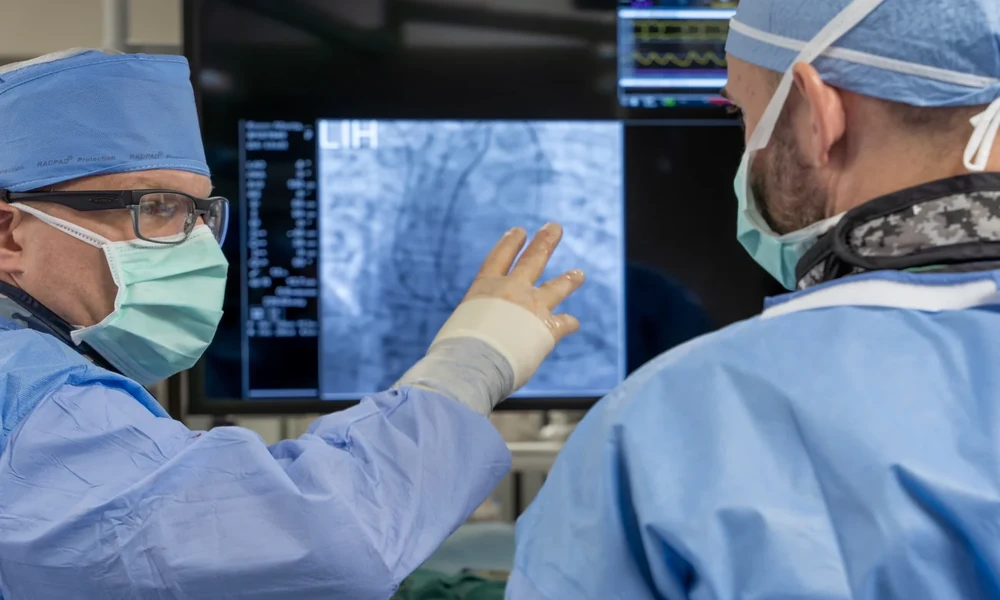
A catheter is usually inserted through a vein in the groin. The team crosses from the right atrium to the left atrium and guides the clip toward the mitral valve using fluoroscopy and transoesophageal echocardiography.
The clip grasps the leaflets at the area of the leak. Before it is released, the team checks how much regurgitation has been reduced and whether the pressure across the valve remains acceptable.
Patients who want a more detailed technical explanation can review a MitraClip procedure guide before their consultation.
What Happens After Treatment?
Hospital recovery is usually shorter than after open-heart surgery when the procedure is uncomplicated. Follow-up echocardiography checks the residual leak and heart function.
Medical therapy does not stop after TEER. Patients with heart failure usually continue long-term treatment for the underlying condition, and the cardiac team may adjust medicines as symptoms and blood pressure change.
The Bottom Line
Living with mitral regurgitation does not mean every patient needs an immediate procedure. Mild or moderate disease may only require monitoring, while severe disease needs closer assessment of symptoms, heart function and treatment timing.
MitraClip becomes an option when the regurgitation is clinically important, the anatomy is suitable and a multidisciplinary team believes TEER offers meaningful benefit compared with surgery or continued medical therapy.
The most important step is not waiting for severe disability before seeking review. Regular follow-up allows changes in symptoms, ventricular function and valve severity to be identified early enough for the full range of treatment options to remain available.